
Is My Neuropathy From Diabetes, or Something Else That Looks Like It?


Diabetes is a common cause of neuropathy, but far from the only one. Thyroid dysfunction, B12 deficiency, certain medications including metformin and acid-reducing drugs, alcohol, and autoimmune conditions can all produce symptoms nearly identical to diabetic neuropathy. When any of these overlap with diabetes, which they frequently do, the true picture is often more complicated than a single diagnosis suggests.
Being handed a diabetic neuropathy diagnosis the moment burning feet and a diabetes history appear together is understandable, but it is worth confirming that other contributors have not been overlooked.
The Mechanism
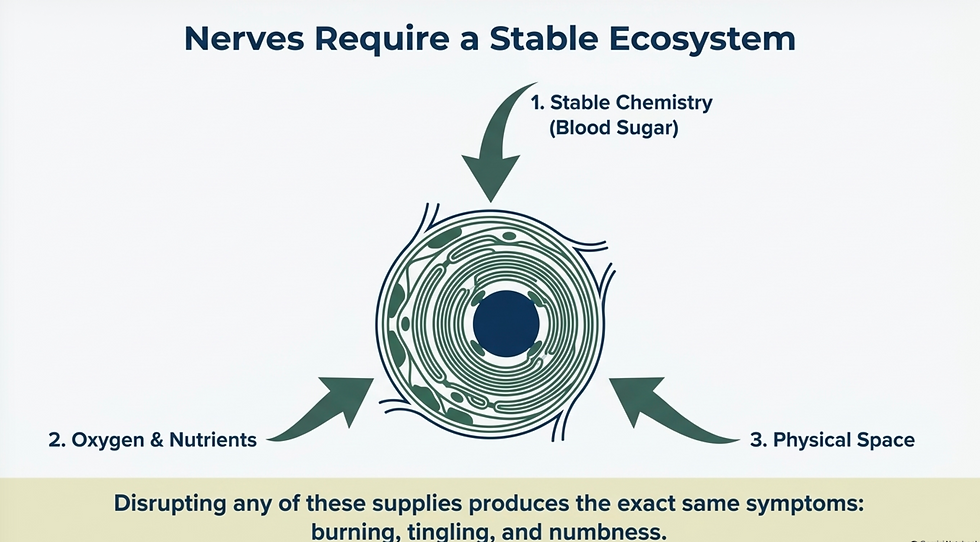
Peripheral nerves depend on a steady supply of oxygen, nutrients, and stable chemistry to function, and several processes besides blood sugar can disrupt that supply in ways that produce the same burning, tingling, and numbness. Hypothyroidism causes fluid retention that can physically compress peripheral nerves and also impairs the cellular energy production nerve cells depend on. Vitamin B12 is essential for maintaining the nerve’s protective myelin sheath, and low B12 produces a neuropathy that can look clinically identical to diabetic neuropathy, which matters directly for people with diabetes, since metformin, the most commonly prescribed diabetes medication, independently lowers B12 levels. A review on this exact overlap notes that vitamin B12 deficiency has similar symptoms to diabetic neuropathy, which itself affects 40 to 50 percent of patients with type 2 diabetes at some stage, making the two easy to confuse or miss entirely when only one is considered.

The picture becomes more layered still when other common medications are involved. A detailed review on this topic describes metformin combined with either acid-reducing medications called proton pump inhibitors or H2 receptor antagonists as a polypharmacy recipe for neuropathy through vitamin B12 depletion, since both drug classes independently reduce B12 absorption and are frequently prescribed together. A separate review in the journal Advances in Nutrition confirms that proton pump inhibitors, H2 receptor antagonists, and metformin can each reduce B12 levels by interfering with its absorption, though researchers note that more precise testing beyond a standard B12 blood level is often needed to confirm a true functional deficiency. Chronic alcohol use and autoimmune conditions such as Sjogren’s syndrome round out the list of commonly overlooked contributors.

Any of these can exist alongside diabetes rather than instead of it, which means a diabetic neuropathy diagnosis does not rule out a second, treatable contributor working in parallel.
When It’s Something More Serious
Rapidly progressing weakness or numbness, especially if spreading quickly or affecting both sides of the body within days rather than months, needs prompt evaluation. Significant unintentional weight loss alongside new nerve symptoms, or symptoms accompanied by vision changes, also warrant a timely medical workup.
How This Gets Addressed
Since more than one contributor is common, a thorough workup looks beyond blood sugar alone.

Naturopathic medicine evaluates thyroid function, B12 and other nutrient levels, medication history, and autoimmune markers to identify every contributor rather than stopping at the first explanation found, and builds supplementation or treatment recommendations around what the results actually show.
Chiropractic care assesses for compression along the nerve’s path that can compound any metabolic driver.
Dry needling and massage therapy address muscular tension contributing to nerve irritation, and physical therapy supports strength and balance affected by sensory changes. Any changes to diabetes or acid-reducing medications should be made with your prescribing physician.
You can learn more about our full approach to neuropathy here.
Most patients see additional improvement once every contributing factor, not only blood sugar, is identified and addressed, although how much symptoms resolve depends on how long each factor was present and whether nerve damage from any one of them has become advanced.

Written By:
Dr. Jason Winkelmann
Naturopathic doctor, Chiropractor, Chronic Pain Specialist, and Educator
Frequently Asked Questions
Can I have B12 deficiency even if my diabetes is well controlled?
Yes. B12 deficiency from metformin use, acid-reducing medications, diet, or absorption problems develops independently of how well blood sugar is managed. It is worth having B12 checked directly rather than assuming good blood sugar control rules it out.
Should I ask my doctor to test for something other than diabetes if I have neuropathy?
If you have risk factors beyond diabetes, such as long-term metformin or acid-reducing medication use, a vegetarian or vegan diet, significant alcohol use, or thyroid symptoms, it is reasonable to ask specifically about B12, thyroid function, and other causes rather than assuming diabetes fully explains your symptoms.
Is a normal B12 blood level enough to rule out B12-related neuropathy?
Not always. Research notes that standard B12 blood tests do not always capture a true functional deficiency, and more specific markers are sometimes needed to confirm the diagnosis. If B12-related neuropathy is still suspected despite a normal level, discussing further testing with your physician is reasonable.


Comments